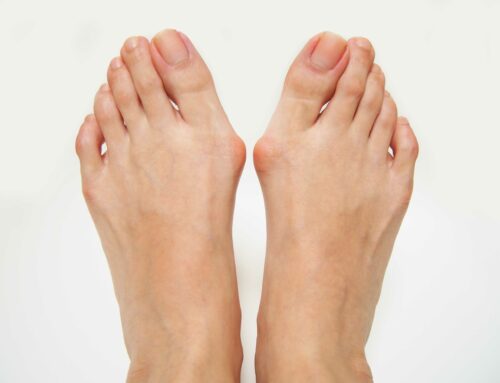
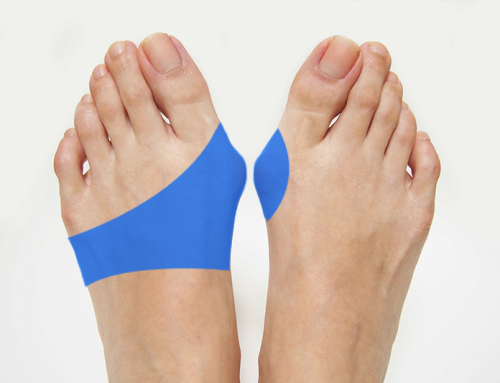
Short answer: Lapiplasty® is a branded Lapidus-style fusion of a midfoot joint, usually held with permanent plates and screws. We do not perform Lapiplasty. We use minimally invasive bunionectomy: a 3D correction that cuts, shifts, and rotates the first metatarsal through a small incision and holds it with a temporary pin. Traditional open bunionectomy uses a larger incision and often leaves screws in the foot. No single operation is right for every foot. We choose after we see your exam and weight-bearing X-rays.
At The Bunion Cure in Littleton, Dr. Jordan Sullivan has performed more than 3,000 minimally invasive bunion corrections since 2019. In our experience, appropriate candidates get the same or better results than traditional open surgery, with an easier recovery in most cases. We will tell you if a different approach suits your foot better.
Side-by-side comparison
Minimally invasive bunionectomy
Osteotomy with temporary pin
- IncisionAbout 1/4 inch; less soft-tissue exposure
- FixationTemporary pin, commonly removed around 4 weeks; no plates or screws in our standard approach
- AnesthesiaLocal numbing in our typical procedure; no breathing tubes, no IVs
- Walking & recoveryWalk out the same day in a surgical sandal, with limits. Almost all patients can drive home after surgery unless they have taken Ativan, narcotic pain medication, or anything else that impairs driving. Almost everyone is in a roomy normal shoe by about 4 weeks
- Who it suitsMost mild to severe bunions without significant midfoot instability or advanced big-toe arthritis; patients who want to stay mobile. For extremely severe bunions, we say up front that a small bump may remain and that the goal is about 80–90% improvement, not perfection
Lapiplasty
Lapidus-style fusion
- IncisionLarger incision and more dissection to reach and fuse the joint, often 3 inches or more
- FixationTypically permanent titanium plates and screws
- AnesthesiaVaries by surgeon and facility; often sedation or general anesthesia. When general anesthesia is used, patients need a friend or family member to drive them home, and typically cannot drive while the right foot is in a boot.
- Walking & recoveryProtected, often in a boot; fusion healing is generally longer and more protected. Exact rules vary by surgeon
- Who it suitsSelected feet with true first tarsometatarsal joint instability, or some revision cases
Traditional open bunionectomy
Open osteotomy
- IncisionLarger open incision over the big toe joint
- FixationUsually permanent screws, sometimes a plate
- AnesthesiaVaries by surgeon and facility
- Walking & recoveryProtected walking in a post-op shoe or boot; rules vary with the cut and fixation
- Who it suitsSurgeons and patients who prefer an open technique; some mild-to-moderate deformities
Swipe sideways to see every column on smaller screens.
| Minimally invasive bunionectomy | Lapiplasty (Lapidus-style fusion) | Traditional open bunionectomy | |
|---|---|---|---|
| What it is | An osteotomy: a 3D correction in which the first metatarsal is cut, shifted, rotated, and aligned in all three planes | A fusion of the first tarsometatarsal (midfoot) joint | An open osteotomy (for example a chevron or scarf-type cut), sometimes with bump removal |
| Incision | About 1/4 inch; less soft-tissue exposure | Larger incision and more dissection to reach and fuse the joint, often 3 inches or more | Larger open incision over the big toe joint |
| Bone fixation | Temporary pin, commonly removed around 4 weeks; no plates or screws in our standard approach | Typically permanent titanium plates and screws | Usually permanent screws, sometimes a plate |
| Anesthesia (typical) | Local numbing in our typical procedure; no breathing tubes, no IVs | Varies by surgeon and facility; often sedation or general anesthesia. When general anesthesia is used, patients need a friend or family member to drive them home, and typically cannot drive while the right foot is in a boot. | Varies by surgeon and facility |
| Time at the center | Plan on about 90 minutes in the building. The operation itself is usually 20 to 30 minutes, or 45 to 60 minutes when combined with other procedures such as multiple hammertoe corrections | Varies by surgeon and facility | Varies by surgeon and facility |
| Recovery and walking | You walk out the same day in a surgical sandal, with limits. Almost all patients can drive home after surgery unless they have taken Ativan, narcotic pain medication, or anything else that impairs driving. For the first 2 weeks, plan on about 15 minutes per hour on your feet (walking and standing combined). Almost everyone is in a roomy normal shoe by about 4 weeks | Protected, often in a boot; fusion healing is generally longer and more protected. Exact rules vary by surgeon | Protected walking in a post-op shoe or boot; rules vary with the cut and fixation |
| Joint motion | Preserves the midfoot joint | The fused midfoot joint no longer moves | Preserves the midfoot joint |
| Both feet | Sometimes possible in one recovery period, because you can walk after surgery. It depends on your health, deformity, and home support | Because patients often cannot put weight on the foot, surgery is commonly done one foot at a time — so two recovery periods if both feet need surgery. Protocols vary | Varies by surgeon and protocol |
| Who it often suits | Most mild to severe bunions without significant midfoot instability or advanced big-toe arthritis; patients who want to stay mobile. For extremely severe bunions, we say up front that a small bump may remain and that the goal is about 80–90% improvement, not perfection | Selected feet with true first tarsometatarsal joint instability, or some revision cases | Surgeons and patients who prefer an open technique; some mild-to-moderate deformities |
Our experience: Dr. Sullivan has performed more than 3,000 minimally invasive bunion corrections since 2019. We do not publish a clinic-specific recurrence rate or a revision rate. Published literature puts recurrence under 5%, and returns have been uncommon in our experience.
Before & after
These are our own patients’ results — not a head-to-head outcome comparison with Lapiplasty. We don’t perform Lapiplasty, so we only show our own work here. Some swelling is still expected at 8 weeks. Individual results vary. See more in our before & after gallery.
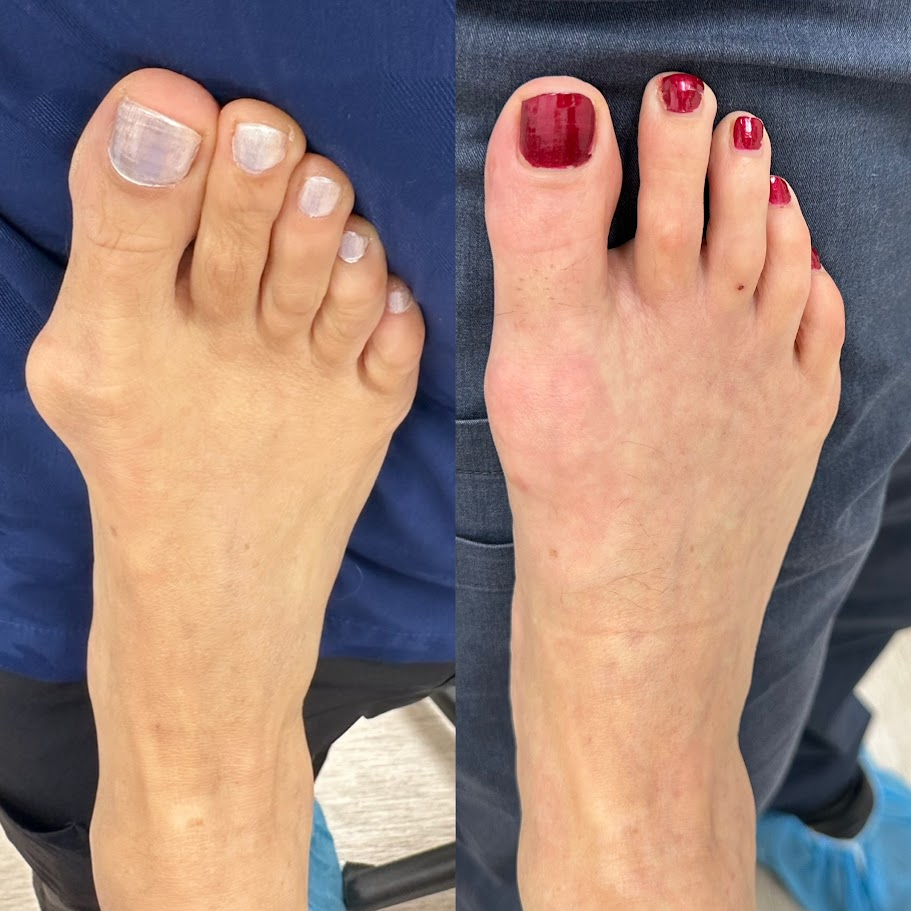
Minimally invasive bunionectomy, before and 8 weeks after.

Severe bunion and hammertoe correction, before and 8 weeks after.
Why we usually lead with minimally invasive bunionectomy
We focus on minimally invasive forefoot surgery because it lets us do a full 3D correction — including rotating the first metatarsal and realigning the sesamoids — through a small incision, without permanent hardware, and usually under local anesthesia, with no breathing tubes and no IVs. Because it is an osteotomy rather than a fusion, the bone heals more like a controlled fracture and the midfoot joint keeps its motion. A smaller incision is not the whole point. The correction is.
Recovery, in brief:
- Everyone walks out the same day in a surgical sandal, never a boot, with limits.
- Almost all patients can drive home after surgery unless they have taken Ativan, narcotic pain medication, or anything else that impairs driving.
- For the first 2 weeks, plan on about 15 minutes per hour on your feet (walking and standing combined).
- Desk-work return is often after a long weekend to about a week, if the foot can be kept elevated. Standing or walking jobs usually need at least 8 weeks.
- The temporary pin is usually removed around 4 weeks. Almost everyone is in normal shoes by about then, usually a loose tennis shoe or slip-on that accommodates some swelling.
- Running, jumping, and court sports wait until later — about 10 to 12 weeks, and only after the surgeon confirms healing. Being in normal shoes at about 4 weeks does not mean you are cleared for high-impact activity.
More detail is on how long after bunion surgery you can drive and our week-by-week recovery page.
When Lapiplasty or another approach may fit better
Lapiplasty is heavily advertised, and that alone does not make it better or worse. A fusion can make sense when the first tarsometatarsal joint is truly unstable, and some revision cases need a different plan. Advanced arthritis in the big toe joint may point to a different operation altogether. If your X-rays show one of these patterns, we will say so and explain your options, including referral when that is the right call.
What decides the right procedure for you
- Weight-bearing X-rays: severity, rotation, and sesamoid position
- Midfoot joint stability and big-toe joint arthritis
- Bone quality, circulation, diabetes control, nicotine use, and neuropathy
- Other problems such as hammertoes or a tailor’s bunion
- Your work, activity goals, and home support during recovery
Learn more: Minimally invasive bunion surgery · Week-by-week recovery · Am I a candidate? · Can I walk after bunion surgery? · Before and after photos · Cost, insurance, and financing
Cost and insurance
We accept Medicare and most major plans. We cannot see Medicaid patients because of Medicaid rules. What you pay depends on your plan and deductible, so we check your benefits before surgery. If you have out-of-pocket costs, patient financing is available for qualifying patients. Questions to ask before surgery are on our cost, insurance, and financing page.
Frequently asked questions
Does The Bunion Cure perform Lapiplasty?
No. We use minimally invasive bunion correction. Patients walk out the same day in a surgical sandal. Almost all patients can drive home after surgery unless they have taken Ativan, narcotic pain medication, or anything else that impairs driving. Dr. Sullivan can go over which approach fits your foot at your consult.
Is Lapiplasty better than minimally invasive bunion surgery?
Not automatically. They are different operations. Lapiplasty fuses a midfoot joint. Minimally invasive bunionectomy corrects the bone with a cut and a temporary pin. The better choice depends on your anatomy, especially midfoot stability and arthritis.
Is minimally invasive bunionectomy also a 3D correction?
Yes. We shift the metatarsal and correct its rotation so the bone is realigned in all three planes — the same goal Lapiplasty markets as 3D — without fusing a midfoot joint.
Which bunion surgery has the fastest recovery?
In general, an osteotomy heals faster than a fusion. With our minimally invasive approach, you walk the same day in a post-op shoe with limits, the pin usually comes out around 4 weeks, and almost every patient is in a roomy normal shoe by about then. Higher-impact activity waits for clearance, often around 10 to 12 weeks.
Will my bunion come back?
Returns are uncommon in our experience. Published literature puts recurrence under 5%; we do not claim a clinic-specific recurrence or revision statistic. For extremely severe bunions, we tell patients up front that a small bump may remain. In those cases the goal is about 80–90% improvement, not perfection.
Do I need plates or screws?
Not in our standard minimally invasive approach. We use a temporary pin that is usually removed around 4 weeks. Lapiplasty and many traditional open procedures use permanent hardware.
Am I awake for surgery?
Our typical procedure uses local anesthesia, like at the dentist, with no breathing tubes and no IVs, and you stay awake. Almost all patients can drive home after surgery unless they have taken Ativan, narcotic pain medication, or anything else that impairs driving. Your plan is set after we review your health history. Plan on about 90 minutes in the building.
Can you fix both feet at once?
Sometimes. It depends on your health, deformity, and home support. We will talk through whether to stage or combine them.
Where are you located?
Our surgical suite is at 13402 W Coal Mine Ave, Suite 310, Littleton, CO 80127, a short drive from Denver and the southwest metro area.
Get a straight answer about your foot
Bring your questions, and your X-rays if you have them. The consultation is free, X-rays included. We will tell you which approach fits your bunion and why. Request your free consultation or call 720-758-6760, weekdays 8:30 AM to 4:30 PM.
Medically reviewed by Jordan Sullivan, DPM · Updated November 18, 2026

Reviewed By Dr. Sullivan
Dr. Jordan Sullivan, DPM, is a podiatrist board certified by the American Board of Podiatric Medicine (ABPM) at Northwest Surgery Center specializing in minimally invasive foot and ankle procedures. He’s passionate about helping patients get back on their feet faster with less downtime.
Learn more about Dr. Sullivan here.